CDC U.S. Standard Certificate of Live Birth Template
CDC U.S. Standard Certificate of Live Birth Template
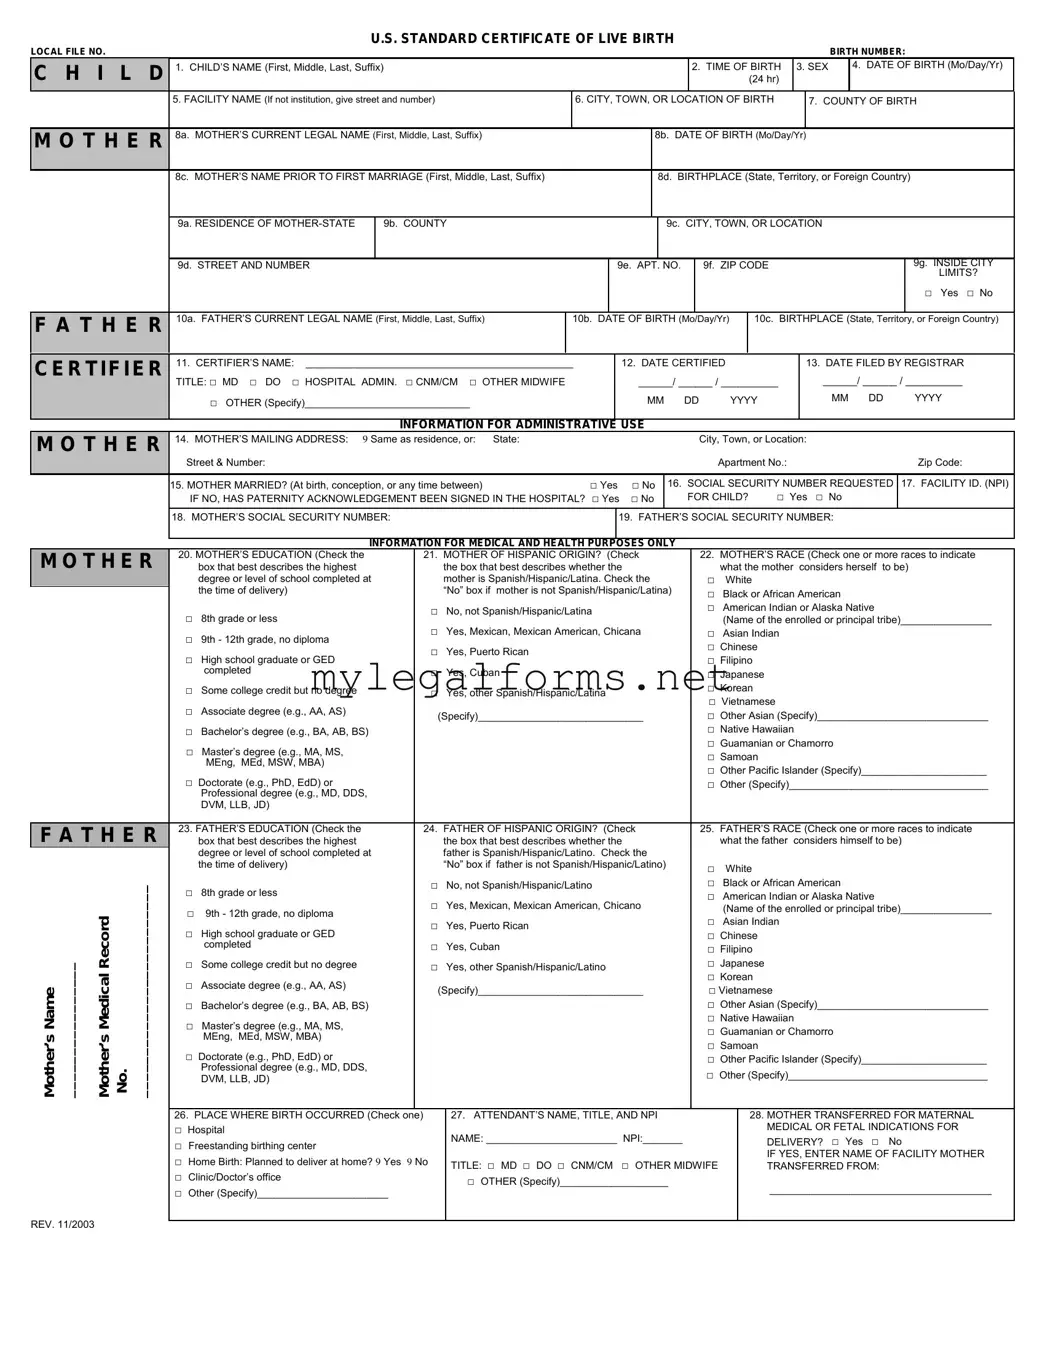
The CDC U.S. Standard Certificate of Live Birth form serves as a critical document in the registration of births across the United States. This form captures essential information about the newborn, including the child's name, date and place of birth, and details about the parents. It also includes demographic information, such as the parents' ages, education levels, and places of birth, which contribute to vital statistics and public health research. The form is designed to ensure uniformity in birth data collection, facilitating accurate tracking of birth trends and health outcomes. Additionally, it plays a significant role in establishing identity and citizenship for the newborn. By standardizing the information collected, the CDC aims to enhance the quality of data that informs health policies and programs nationwide. Understanding the components and significance of this form is vital for parents, healthcare providers, and public health officials alike.
When filling out the CDC U.S. Standard Certificate of Live Birth form, keep the following key points in mind:
Following these steps will help ensure a smooth process when obtaining a birth certificate.
Broward Animal Care and Adoption - Animal owners may need to present this certificate for boarding.
Miscellaneous Information - Payments for legal services, even to corporations, must be reported using this form.
The CDC U.S. Standard Certificate of Live Birth form is a crucial document for registering a birth in the United States. Alongside this form, several other documents and forms may be required or useful in various situations related to birth registration, identity verification, and legal matters. Below is a list of commonly used forms and documents that complement the birth certificate.
Understanding these documents can simplify the process of managing a newborn's legal and healthcare needs. Each form plays a vital role in ensuring that the rights and needs of the child and parents are met effectively.
When filling out the CDC U.S. Standard Certificate of Live Birth form, it’s important to ensure that all information is accurate and complete. Here are some guidelines to help you navigate the process.
Following these tips can help make the process smoother and ensure that your certificate is completed correctly.
Filling out the CDC U.S. Standard Certificate of Live Birth form can be straightforward, but mistakes often occur. One common error is providing incorrect or incomplete information about the parents. Ensure that names, addresses, and dates of birth are accurate. Missing or incorrect details can lead to delays in processing and may require additional follow-up.
Another frequent mistake is failing to sign the form. Both parents must provide their signatures. If one parent is unavailable, this should be noted clearly. Without the necessary signatures, the form cannot be processed, which can cause significant delays in obtaining the official birth certificate.
Some people overlook the importance of the child's information. It is crucial to accurately record the child’s full name, date of birth, and sex. Errors in this section can lead to confusion later on, especially when it comes to legal documents and identification. Double-check this information before submission.
Many individuals also forget to include the attending physician or midwife's information. This section is vital for verification purposes. Ensure that the name, address, and license number of the healthcare provider are included. Omitting this information can result in additional complications and may delay the issuance of the birth certificate.
Lastly, not following the specific instructions for submitting the form is a common oversight. Each state may have different requirements for submission, including deadlines and acceptable methods (mail, online, in-person). Be sure to review these requirements carefully to avoid unnecessary delays in processing.
| Fact Name | Description |
|---|---|
| Purpose | The CDC U.S. Standard Certificate of Live Birth form is used to record the birth of a child in the United States. It serves as an official document for vital statistics and is essential for obtaining a birth certificate. |
| Standardization | This form is standardized across the United States, ensuring consistency in the information collected regarding births. It facilitates the collection of vital statistics at both state and national levels. |
| State Variations | While the CDC provides a standard form, individual states may have specific variations or additional requirements. Each state governs its own birth registration process under laws such as the Vital Statistics Act. |
| Required Information | The form requires detailed information, including the child's name, date of birth, place of birth, and parental information. Accurate completion is crucial for legal identification and record-keeping. |
| Legal Use | The completed form is necessary for obtaining a certified birth certificate, which is often required for legal purposes, such as applying for a passport or enrolling in school. |
U.S. STANDARD CERTIFICATE OF LIVE BIRTH
LOCAL FILE NO. |
|
|
|
|
|
|
BIRTH NUMBER: |
|
C H I L D |
1. CHILD’S NAME (First, Middle, Last, Suffix) |
|
|
2. TIME OF BIRTH |
3. SEX |
|
4. DATE OF BIRTH (Mo/Day/Yr) |
|
|
|
|
(24 hr) |
|
|
|
|
|
|
5. FACILITY NAME (If not institution, give street and number) |
6. CITY, TOWN, OR LOCATION OF BIRTH |
|
7. COUNTY OF BIRTH |
||||
|
|
|
8b. DATE OF BIRTH (Mo/Day/Yr) |
|
|
|
||
M O T H E R |
8a. MOTHER’S CURRENT LEGAL NAME (First, Middle, Last, Suffix) |
|
|
|
|
|||
|
|
|
|
|
|
|
|
|
8c. MOTHER’S NAME PRIOR TO FIRST MARRIAGE (First, Middle, Last, Suffix)
8d. BIRTHPLACE (State, Territory, or Foreign Country)
|
9a. RESIDENCE OF |
|
9b. COUNTY |
|
|
|
|
|
9c. CITY, TOWN, OR LOCATION |
|
|
|||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||
|
9d. STREET AND NUMBER |
|
|
|
|
9e. APT. |
NO. |
|
9f. ZIP CODE |
|
|
|
|
9g. INSIDE CITY |
||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
LIMITS? |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
□ Yes □ No |
|
|
|
|
|
|
|
|
|
|
|
|
|||||||
F A T H E R |
10a. FATHER’S CURRENT LEGAL NAME (First, Middle, Last, Suffix) |
10b. DATE OF BIRTH (Mo/Day/Yr) |
|
10c. BIRTHPLACE (State, Territory, or Foreign Country) |
||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
||||||||
CERTIFIER |
11. CERTIFIER’S NAME: _______________________________________________ |
|
12. DATE CERTIFIED |
|
|
|
13. DATE FILED BY REGISTRAR |
|||||||||||
|
TITLE: □ MD □ DO □ HOSPITAL ADMIN. □ CNM/CM □ OTHER MIDWIFE |
|
|
|
______/ ______ / __________ |
|
______/ ______ / __________ |
|||||||||||
|
□ OTHER (Specify)_____________________________ |
|
|
|
MM |
DD |
YYYY |
|
|
MM DD |
|
YYYY |
||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
|
|
|
INFORMATION FOR ADMINISTRATIVE |
USE |
|
|
|
|
|
|
|
|
|
|||||
M O T H E R |
14. MOTHER’S MAILING ADDRESS: |
9 Same as residence, or: State: |
|
|
|
|
|
|
|
City, Town, or Location: |
|
|
|
|||||
|
Street & Number: |
|
|
|
|
|
|
|
|
|
Apartment No.: |
|
|
Zip Code: |
||||
|
15. MOTHER MARRIED? (At birth, conception, or any time between) |
□ Yes |
□ No |
16. SOCIAL SECURITY NUMBER REQUESTED |
17. FACILITY ID. (NPI) |
|||||||||||||
|
IF NO, HAS PATERNITY ACKNOWLEDGEMENT BEEN SIGNED IN THE HOSPITAL? □ Yes |
□ No |
|
FOR CHILD? |
□ Yes |
□ No |
|
|
||||||||||
|
18. MOTHER’S SOCIAL SECURITY NUMBER: |
|
|
19. FATHER’S SOCIAL SECURITY NUMBER: |
|
|
||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||
|
|
INFORMATION FOR MEDICAL AND HEALTH PURPOSES ONLY |
|
|
|
|
|
|
|
|
|
|||||||
M O T H E R
F A T H E R
Mother’s Name ________________ |
Mother’s Medical Record No. _________________________ |
20. MOTHER’S EDUCATION (Check the |
21. MOTHER OF HISPANIC ORIGIN? (Check |
|||
|
box that best describes the highest |
|
the box that best describes whether the |
|
|
degree or level of school completed at |
|
mother is Spanish/Hispanic/Latina. Check the |
|
|
the time of delivery) |
|
“No” box if mother is not Spanish/Hispanic/Latina) |
|
□ |
8th grade or less |
□ |
No, not Spanish/Hispanic/Latina |
|
□ Yes, Mexican, Mexican American, Chicana |
||||
□ |
9th - 12th grade, no diploma |
|||
□ |
Yes, Puerto Rican |
|||
□ |
High school graduate or GED |
|||
□ |
|
|||
|
completed |
Yes, Cuban |
||
□ |
Some college credit but no degree |
□ |
Yes, other Spanish/Hispanic/Latina |
|
□ Associate degree (e.g., AA, AS) |
|
(Specify)_____________________________ |
||
|
|
|
||
□Bachelor’s degree (e.g., BA, AB, BS)
□Master’s degree (e.g., MA, MS, MEng, MEd, MSW, MBA)
□Doctorate (e.g., PhD, EdD) or Professional degree (e.g., MD, DDS, DVM, LLB, JD)
23. FATHER’S EDUCATION (Check the |
24. FATHER OF HISPANIC ORIGIN? (Check |
|||
|
box that best describes the highest |
|
the box that best describes whether the |
|
|
degree or level of school completed at |
|
father is Spanish/Hispanic/Latino. Check the |
|
|
the time of delivery) |
|
“No” box if father is not Spanish/Hispanic/Latino) |
|
□ |
8th grade or less |
□ |
No, not Spanish/Hispanic/Latino |
|
□ Yes, Mexican, Mexican American, Chicano |
||||
□ |
9th - 12th grade, no diploma |
|||
□ |
Yes, Puerto Rican |
|||
□ |
High school graduate or GED |
|||
□ |
|
|||
|
completed |
Yes, Cuban |
||
□ |
Some college credit but no degree |
□ |
Yes, other Spanish/Hispanic/Latino |
|
□ Associate degree (e.g., AA, AS) |
|
(Specify)_____________________________ |
||
|
|
|
||
□Bachelor’s degree (e.g., BA, AB, BS)
□Master’s degree (e.g., MA, MS, MEng, MEd, MSW, MBA)
□Doctorate (e.g., PhD, EdD) or Professional degree (e.g., MD, DDS, DVM, LLB, JD)
22.MOTHER’S RACE (Check one or more races to indicate what the mother considers herself to be)
□White
□Black or African American
□American Indian or Alaska Native
(Name of the enrolled or principal tribe)________________
□Asian Indian
□Chinese
□Filipino
□Japanese
□Korean
□Vietnamese
□Other Asian (Specify)______________________________
□Native Hawaiian
□Guamanian or Chamorro
□Samoan
□Other Pacific Islander (Specify)______________________
□Other (Specify)___________________________________
25.FATHER’S RACE (Check one or more races to indicate what the father considers himself to be)
□White
□Black or African American
□American Indian or Alaska Native
(Name of the enrolled or principal tribe)________________
□Asian Indian
□Chinese
□Filipino
□Japanese
□Korean
□Vietnamese
□Other Asian (Specify)______________________________
□Native Hawaiian
□Guamanian or Chamorro
□Samoan
□Other Pacific Islander (Specify)______________________
□Other (Specify)___________________________________
26. PLACE WHERE BIRTH OCCURRED (Check one) |
27. ATTENDANT’S NAME, TITLE, AND NPI |
28. MOTHER TRANSFERRED FOR MATERNAL |
|
□ Hospital |
NAME: _______________________ NPI:_______ |
MEDICAL OR FETAL INDICATIONS FOR |
|
□ Freestanding birthing center |
DELIVERY? □ Yes □ No |
||
|
IF YES, ENTER NAME OF FACILITY MOTHER |
||
□ Home Birth: Planned to deliver at home? 9 Yes 9 No |
TITLE: □ MD □ DO □ CNM/CM □ OTHER MIDWIFE |
||
TRANSFERRED FROM: |
|||
□ Clinic/Doctor’s office |
□ OTHER (Specify)___________________ |
_______________________________________ |
|
□ Other (Specify)_______________________ |
|||
|
REV. 11/2003

|
MOTHER |
29a. DATE OF FIRST PRENATAL CARE VISIT |
|
29b. DATE OF LAST PRENATAL CARE VISIT |
30. TOTAL NUMBER OF PRENATAL VISITS FOR THIS PREGNANCY |
||||||||||||||||||
|
______ /________/ __________ □ No Prenatal Care |
|
|
______ /________/ __________ |
|
|
|
|
|
|
|
|
|||||||||||
|
|
M M |
D D |
|
|
|
YYYY |
|
|
|
M M |
D D |
YYYY |
|
|
_________________________ (If none, enter A0".) |
|||||||
|
|
|
|
|
|
|
|
|
|
|
|
||||||||||||
|
|
31. MOTHER’S HEIGHT |
32. MOTHER’S |
PREPREGNANCY WEIGHT |
33. MOTHER’S WEIGHT |
AT DELIVERY |
34. DID MOTHER GET WIC FOOD FOR HERSELF |
||||||||||||||||
|
|
_______ (feet/inches) |
_________ (pounds) |
|
|
_________ (pounds) |
|
|
DURING THIS PREGNANCY? □ Yes □ No |
||||||||||||||
|
|
35. NUMBER OF PREVIOUS |
36. NUMBER OF OTHER |
37. CIGARETTE SMOKING BEFORE AND DURING PREGNANCY |
|
38. PRINCIPAL SOURCE OF |
|||||||||||||||||
|
|
LIVE BIRTHS (Do not include |
PREGNANCY OUTCOMES |
For each time period, enter either the number of cigarettes or the |
|
PAYMENT FOR THIS |
|||||||||||||||||
|
|
this child) |
|
|
|
|
(spontaneous or induced |
number of packs of cigarettes smoked. IF NONE, ENTER A0". |
|
DELIVERY |
|||||||||||||
|
|
|
|
|
|
|
|
|
losses or ectopic pregnancies) |
Average number of cigarettes or packs of cigarettes smoked per day. |
□ Private Insurance |
||||||||||||
|
|
35a. |
Now Living |
|
35b. Now Dead |
36a. Other Outcomes |
|
||||||||||||||||
|
|
Number _____ |
|
|
Number _____ |
Number _____ |
|
|
|
|
|
|
|
# of cigarettes |
# of packs |
□ Medicaid |
|||||||
|
|
|
|
|
|
|
Three Months Before Pregnancy |
_________ |
|
OR |
________ |
□ |
|||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
First Three Months of Pregnancy |
_________ |
|
OR |
________ |
□ Other |
|||||
|
|
□ None |
|
|
|
□ None |
□ None |
|
|
|
Second Three Months of Pregnancy _________ |
OR |
________ |
||||||||||
|
|
|
|
|
|
|
|
(Specify) _______________ |
|||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
Third Trimester of Pregnancy |
_________ |
OR |
________ |
|||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||||||
|
|
|
|
|
|
|
|
|
|
||||||||||||||
|
|
35c. DATE OF LAST LIVE BIRTH |
36b. DATE OF LAST OTHER |
39. DATE LAST NORMAL MENSES BEGAN |
|
40. MOTHER’S MEDICAL RECORD NUMBER |
|||||||||||||||||
|
|
|
_______/________ |
PREGNANCY OUTCOME |
______ /________/ __________ |
|
|
|
|
|
|
||||||||||||
|
|
|
|
MM |
Y Y Y Y |
_______/________ |
M M |
D D |
YYYY |
|
|
|
|
|
|
||||||||
|
|
|
|
|
|
|
|
|
MM |
Y Y Y Y |
|
|
|
|
|
|
|
|
|
|
|
||
|
|
|
|
|
|
|
|
|
|||||||||||||||
|
MEDICAL |
41. RISK FACTORS IN THIS PREGNANCY |
|
43. OBSTETRIC PROCEDURES (Check all that apply) |
46. METHOD OF DELIVERY |
||||||||||||||||||
|
|
|
(Check all that apply) |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||
|
AND |
Diabetes |
|
|
|
|
|
|
|
□ Cervical cerclage |
|
|
|
|
|
|
A. Was delivery with forceps attempted but |
||||||
|
HEALTH |
□ |
|
Prepregnancy |
(Diagnosis prior to this pregnancy) |
|
□ Tocolysis |
|
|
|
|
|
|
|
unsuccessful? |
|
|||||||
|
□ |
|
Gestational |
|
(Diagnosis in this pregnancy) |
|
|
External cephalic version: |
|
|
|
|
|
|
□ Yes |
□ No |
|||||||
|
INFORMATION |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
B. Was delivery with vacuum extraction attempted |
||||||
|
Hypertension |
|
|
|
|
|
|
|
□ Successful |
|
|
|
|
|
|
||||||||
|
|
□ |
|
Prepregnancy |
(Chronic) |
|
|
|
□ Failed |
|
|
|
|
|
|
|
but unsuccessful? |
||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||||||||
|
|
□ |
|
Gestational |
(PIH, preeclampsia) |
|
|
□ None of the above |
|
|
|
|
|
|
|
□ Yes |
□ No |
||||||
|
|
□ |
|
Eclampsia |
|
|
|
|
|
|
|
|
|
|
|
C. Fetal presentation at birth |
|||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
|
|
□ Previous preterm birth |
|
|
|
|
|
|
|
|
|
|
|
□ |
Cephalic |
|
|||||||
|
|
|
|
44. ONSET OF LABOR (Check all that apply) |
|
|
|
||||||||||||||||
|
|
|
|
|
|
□ |
Breech |
|
|
||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||
|
|
□ Other previous poor pregnancy outcome (Includes |
|
□ Premature Rupture of the Membranes (prolonged, ∃12 hrs.) |
□ |
Other |
|
|
|||||||||||||||
|
|
perinatal death, |
|
|
|
|
|
|
|
|
|
D. Final route and method of delivery (Check one) |
|||||||||||
|
|
growth restricted birth) |
|
|
□ Precipitous Labor (<3 hrs.) |
|
|
|
|
||||||||||||||
|
|
|
|
|
|
|
|
□ Vaginal/Spontaneous |
|||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
|
|
□ Pregnancy resulted from infertility |
|
□ Prolonged Labor (∃ 20 hrs.) |
|
|
|
|
□ Vaginal/Forceps |
||||||||||||||
|
|
check all that apply: |
|
|
|
|
|
|
|
|
|
|
|
□ Vaginal/Vacuum |
|||||||||
|
|
□ |
□ None of the above |
|
|
|
|
|
|
□ Cesarean |
|
||||||||||||
|
|
|
|
Intrauterine insemination |
|
|
|
|
|
|
|
|
|
|
|
|
If cesarean, was a trial of labor attempted? |
||||||
|
|
□ Assisted reproductive technology (e.g., in vitro |
|
|
|
|
|
|
|
|
|
|
|
□ Yes |
|
|
|||||||
|
|
|
45. CHARACTERISTICS OF LABOR AND DELIVERY |
|
|
|
|
|
|||||||||||||||
|
|
|
|
fertilization (IVF), gamete intrafallopian |
|
|
|
|
□ No |
|
|
||||||||||||
|
|
|
|
|
|
|
(Check all that |
apply) |
|
|
|
|
|
|
|
||||||||
|
|
|
|
transfer |
(GIFT)) |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||
|
|
|
|
|
|
□ |
Induction of labor |
|
|
|
|
|
|
47. MATERNAL MORBIDITY (Check all that apply) |
|||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||||
|
|
□ Mother had a previous cesarean delivery |
|
|
|
|
|
|
|
(Complications associated with labor and |
|||||||||||||
|
|
|
□ |
Augmentation of labor |
|
|
|
|
|
||||||||||||||
|
|
|
|
If yes, how many __________ |
|
|
|
|
|
|
|
delivery) |
|
|
|||||||||
|
|
|
|
|
|
□ |
|
|
|
|
|
□ |
Maternal transfusion |
||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||||
|
|
□ None of the above |
|
|
□ Steroids (glucocorticoids) for fetal lung maturation |
|
|
□ Third or fourth degree perineal laceration |
|||||||||||||||
|
|
42. INFECTIONS PRESENT AND/OR TREATED |
|
|
received by the mother prior to delivery |
|
|
|
|
□ |
Ruptured uterus |
||||||||||||
|
|
DURING THIS |
PREGNANCY (Check all that apply) |
□ Antibiotics received by the mother during labor |
|
|
□ |
Unplanned hysterectomy |
|||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
□ Clinical chorioamnionitis diagnosed during labor or |
□ Admission to intensive care unit |
|||||||||||
|
|
□ |
Gonorrhea |
|
|
|
|
|
maternal temperature >38°C (100.4°F) |
|
|
□ Unplanned operating room procedure |
|||||||||||
|
|
□ |
Syphilis |
|
|
|
|
|
|
□ Moderate/heavy meconium staining of the amniotic fluid |
|
following delivery |
|||||||||||
|
|
□ |
Chlamydia |
|
|
|
|
□ Fetal intolerance of labor such that one or more of the |
□ None of the above |
||||||||||||||
|
|
□ |
Hepatitis B |
|
|
|
|
|
following actions was taken: |
|
|
|
|
||||||||||
|
|
□ |
Hepatitis C |
|
|
|
|
|
measures, further fetal assessment, or operative delivery |
|
|
|
|
||||||||||
|
|
|
|
|
|
□ Epidural or spinal anesthesia during labor |
|
|
|
|
|
|
|||||||||||
|
|
□ None of the above |
|
|
|
|
|
|
|
|
|||||||||||||
|
|
|
|
□ None of the above |
|
|
|
|
|
|
|
|
|
|
|||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
NEWBORN
Mother’s Name ________________ |
Mother’s Medical Record No. ____________________ |
NEWBORN INFORMATION
48. NEWBORN MEDICAL RECORD NUMBER |
54. ABNORMAL CONDITIONS OF THE NEWBORN |
55. CONGENITAL ANOMALIES OF THE NEWBORN |
||||||
|
|
|
(Check all that apply) |
□ |
|
(Check all that apply) |
||
49. BIRTHWEIGHT (grams preferred, specify unit) |
□ |
Assisted ventilation required immediately |
Anencephaly |
|
||||
|
□ |
Meningomyelocele/Spina bifida |
||||||
______________________ |
|
following delivery |
□ |
Cyanotic congenital heart disease |
||||
9 grams 9 lb/oz |
□ |
|
|
|
□ |
Congenital diaphragmatic hernia |
||
|
Assisted ventilation required for more than |
|||||||
|
□ |
Omphalocele |
|
|||||
|
|
six hours |
|
|||||
50. OBSTETRIC ESTIMATE OF GESTATION: |
|
□ |
Gastroschisis |
|
||||
|
|
|
|
|
||||
_________________ (completed weeks) |
□ |
NICU admission |
□ |
Limb reduction defect (excluding congenital |
||||
|
|
|
|
|
|
amputation and dwarfing syndromes) |
||
|
□ |
Newborn given surfactant replacement |
□ Cleft Lip with or without Cleft Palate |
|||||
|
□ |
Cleft Palate alone |
|
|||||
|
|
therapy |
|
|||||
51. APGAR SCORE: |
|
|
||||||
|
|
|
|
□ |
Down Syndrome |
|
||
Score at 5 minutes:________________________ |
|
|
|
|
|
|||
□ |
Antibiotics received by the newborn for |
|
□ |
Karyotype confirmed |
||||
If 5 minute score is less than 6, |
|
|||||||
Score at 10 minutes: _______________________ |
|
suspected neonatal sepsis |
□ |
□ |
Karyotype pending |
|||
□ |
Seizure or serious neurologic dysfunction |
Suspected chromosomal disorder |
||||||
|
|
□ |
Karyotype confirmed |
|||||
52. PLURALITY - Single, Twin, Triplet, etc. |
□ Significant birth injury (skeletal fracture(s), peripheral |
□ |
□ |
Karyotype pending |
||||
|
Hypospadias |
|
||||||
(Specify)________________________ |
|
nerve |
injury, and/or soft tissue/solid organ hemorrhage |
|
||||
|
□ |
None of the anomalies listed above |
||||||
|
which |
requires intervention) |
||||||
53. IF NOT SINGLE BIRTH - Born First, Second, |
|
|
|
|
|
|
|
|
Third, etc. (Specify) ________________ |
9 None of the above |
|
|
|
|
|||
|
|
|
|
|
||||
|
|
|
|
|
||||
56. WAS INFANT TRANSFERRED WITHIN 24 HOURS OF DELIVERY? 9 Yes 9 No |
57. IS INFANT LIVING AT TIME OF REPORT? |
58. IS THE INFANT BEING |
||||||
IF YES, NAME OF FACILITY INFANT TRANSFERRED |
|
|
□ Yes □ No □ Infant transferred, status unknown |
BREASTFED AT DISCHARGE? |
||||
TO:______________________________________________________ |
|
|
|
|
□ Yes □ No |
|||
|
|
|
|
|
|
|
|
|
Rev. 11/2003
NOTE: This recommended standard birth certificate is the result of an extensive evaluation process. Information on the process and resulting recommendations as well as plans for future
activities is available on the Internet at: http://www.cdc.gov/nchs/vital_certs_rev.htm.